Categories Shoulder Pain

Shoulder Pain at Night: Causes and Treatment Options

Shoulder pain at night showing nighttime discomfort, shoulder inflammation, and difficulty sleeping

Quick Answer

Shoulder pain at night can happen because an irritated shoulder is placed under pressure while you sleep, particularly when lying on the painful side. Common causes include rotator cuff problems, bursitis or tendinopathy, frozen shoulder, shoulder impingement and arthritis. Night pain alone cannot identify the cause. If pain repeatedly wakes you, is getting worse, limits movement or is accompanied by weakness, swelling or an injury, a professional assessment can help determine what is actually causing it.

Quick Summary

  • Nighttime shoulder pain is a symptom with several possible causes.
  • Sleeping directly on a painful shoulder can increase pressure on irritated tissues.
  • Rotator cuff disorders, frozen shoulder, bursitis/tendinopathy, impingement and arthritis are common considerations.
  • Supporting the affected arm and avoiding direct pressure may make sleeping more comfortable.
  • Treatment depends on the diagnosis and may include activity modification, medicines, exercise/physical therapy and selected injections.
  • Persistent sleep-disrupting pain, weakness or loss of movement should be evaluated rather than repeatedly self-treated.
  • Sudden severe pain after injury, deformity, inability to move the arm, or chest/breathing symptoms require urgent medical attention.

Introduction

Shoulder pain can feel surprisingly different at night. A mild ache during the day may become strong enough to wake you when you turn in bed or lie on one side. This does not necessarily mean the condition has suddenly become more serious. Changes in sleeping position, pressure on sensitive tissues and the reduced distraction of daytime activity can make an existing problem much more noticeable. At the same time, recurring night pain can be an important clue that an underlying shoulder condition needs assessment.

Why Does Shoulder Pain Get Worse at Night?

Several factors can contribute. Lying directly on the affected shoulder can compress already irritated tissues. The position of the arm can also place stress on tendons, the bursa or the joint. When you are lying still for a prolonged period, stiffness may become more noticeable. Some shoulder conditions, particularly rotator cuff disorders and frozen shoulder, are also commonly associated with pain that disturbs sleep.

Importantly, night pain does not identify one specific diagnosis. A clinician usually considers the full pattern: where the pain is felt, which movements reproduce it, whether there is weakness or stiffness, whether there was an injury, and how long the symptoms have been present.

Common Causes of Shoulder Pain at Night

Rotator Cuff Problems

Rotator cuff tendinopathy, inflammation or a tear can cause aching shoulder pain that becomes worse at night. Pain with reaching or lifting the arm and weakness can provide additional clues. A rotator cuff problem may develop gradually through overuse or age-related tendon changes, or follow an injury.

Bursitis and Tendinopathy

Inflammation or irritation around the shoulder can become more uncomfortable when the affected area is compressed during side sleeping. Tendon-related pain may also increase with overhead activity or repeated use.

Frozen Shoulder

Frozen shoulder, or adhesive capsulitis, causes pain and progressive stiffness. Night pain can be prominent, and difficulty moving the arm in several directions is an important feature.

Shoulder Impingement

Shoulder impingement describes irritation involving tissues around the shoulder, often producing pain with lifting the arm. Pain can also be worse while sleeping, particularly on the affected side.

Arthritis

Shoulder arthritis can cause pain, stiffness and reduced function. Symptoms may be present both during activity and at rest, and advanced joint changes can interfere with sleep.

Referred or Less Common Causes

Pain felt around the shoulder can sometimes originate outside the shoulder, including from the neck. Rarely, shoulder-area pain can accompany conditions involving the chest or other parts of the body. This is one reason persistent, unusual or associated symptoms should be assessed rather than self-diagnosed.

How to Sleep With Shoulder Pain

For mild or recently developed symptoms, a few practical changes may reduce nighttime discomfort:

  • Avoid sleeping directly on the painful shoulder.
  • Try sleeping on your back or on the opposite side if comfortable.
  • Use a pillow to support the affected arm so it is not hanging unsupported.
  • Consider a semi-upright position if lying flat is uncomfortable.
  • Temporarily reduce activities that clearly aggravate the shoulder.
  • Use heat or cold only in a way that feels appropriate for your symptoms and protects the skin.
  • Use pain medicines only according to the product instructions and your clinician’s advice, particularly if you have other medical conditions or take other medicines.

These steps can improve comfort, but they do not establish the cause of persistent shoulder pain.

How Is Nighttime Shoulder Pain Diagnosed?

Diagnosis generally starts with a medical history and physical examination. The clinician may assess shoulder movement, strength, tenderness and the movements that reproduce symptoms. Imaging such as an X-ray, ultrasound or MRI may be considered when the history and examination suggest a structural problem or when symptoms persist or follow an injury. The appropriate test depends on the suspected cause.

Treatment Options

Conservative and Non-Surgical Care

Treatment should match the underlying problem rather than the time of day when pain occurs. Depending on the diagnosis, care may include activity modification, appropriate pain medication, physical therapy, mobility work and progressive strengthening. Many shoulder conditions can be managed without surgery, but the specific plan should be based on examination and clinical findings.

When Injections May Be Considered

In selected patients, an injection may be considered when pain or inflammation is limiting sleep and function despite appropriate initial care. The target and type of injection depend on the suspected pain generator, such as a joint or bursa. An injection should be considered as part of an overall treatment plan rather than as a substitute for diagnosis and rehabilitation.

When Surgery May Be Considered

Surgery is not automatically required because shoulder pain is worse at night. It may be considered for selected structural injuries, advanced joint disease or symptoms that remain significantly disabling despite appropriate non-surgical management. The decision depends on the diagnosis, severity, functional limitations and response to prior treatment.

When Should You See a Doctor?

Consider a professional evaluation if nighttime shoulder pain repeatedly wakes you, continues to worsen, persists despite reasonable home care, or is associated with weakness, significant stiffness or loss of movement. An assessment is particularly important after a fall or other injury.

Seek urgent medical attention for severe shoulder pain with an obvious deformity, sudden major swelling or inability to move the arm after injury. Shoulder pain accompanied by chest pain/pressure, difficulty breathing, sweating or other concerning symptoms can require emergency assessment because the pain may not be coming from the shoulder itself.

Nexus Advanced Pain Management Expert Summary

Nighttime shoulder pain deserves attention when it becomes recurrent or starts affecting sleep and daily function. The key point is that night pain is a symptom, not a diagnosis. Rotator cuff disorders, frozen shoulder, bursitis, tendinopathy, impingement and arthritis can produce similar complaints, while neck-related or referred pain can sometimes mimic a shoulder problem. A focused clinical assessment helps distinguish these possibilities and guides treatment. For many patients, management can begin with non-surgical measures such as activity modification, rehabilitation and appropriate pain control, with other interventions considered when clinically indicated.

How Nexus Advanced Pain Management Can Help

Nexus Advanced Pain Management provides shoulder pain evaluation and pain-management care in Ahmedabad. Its shoulder pain service describes assessment of different possible causes before selecting treatment, with non-surgical care considered where appropriate. Depending on the diagnosis, the clinic lists medication management, targeted injections, rehabilitation-oriented care and selected interventional options among its services. The appropriate treatment should be determined after a clinical evaluation rather than from nighttime symptoms alone.

Key Takeaways

  • Shoulder pain at night has multiple possible causes and should not be self-diagnosed from night pain alone.
  • Rotator cuff problems, bursitis/tendinopathy, frozen shoulder, impingement and arthritis are important considerations.
  • Changing sleep position and supporting the affected arm may reduce pressure and improve comfort.
  • Persistent pain, weakness or restricted movement warrants assessment.
  • Treatment is diagnosis-dependent and often begins with non-surgical care.
  • Urgent symptoms after injury or symptoms suggesting a cardiac problem need prompt medical attention.

Frequently Asked Questions

Why does my shoulder hurt more at night?

Pressure from sleeping position, reduced movement and an underlying shoulder condition can make symptoms more noticeable at night. Rotator cuff disorders and frozen shoulder are among conditions commonly associated with nighttime pain.

What is the most common cause of shoulder pain at night?

There is no single cause for every person. Rotator cuff-related problems, bursitis/tendinopathy, frozen shoulder, impingement and arthritis are common possibilities.

How should I sleep with shoulder pain?

Avoid putting direct pressure on the painful shoulder. Try the opposite side or your back and use pillows to support the affected arm. A semi-upright position may help some people.

Can a rotator cuff problem cause pain at night?

Yes. Rotator cuff injuries and tendon disorders commonly cause pain that can worsen at night, sometimes together with weakness or pain during overhead movement.

Can frozen shoulder cause nighttime pain?

Yes. Frozen shoulder commonly causes pain and stiffness, and the pain may be worse at night and disturb sleep.

When should I see a doctor for shoulder pain at night?

Arrange an evaluation when pain repeatedly disrupts sleep, persists or worsens, limits movement, or is associated with weakness. Seek urgent care after significant injury or for severe symptoms.

Can shoulder pain at night be treated without surgery?

Many shoulder conditions can initially be managed with non-surgical approaches such as activity modification, appropriate medication, physical therapy and selected injections. The right approach depends on the diagnosis.

Could shoulder pain actually come from the neck?

Yes. Some neck-related nerve problems can refer pain toward the shoulder. A clinical assessment can help distinguish a shoulder problem from referred pain.

Can I use pain medicine before bed?

Some people use over-the-counter pain medicines for short-term symptom relief, but suitability depends on medical history, other medicines and the specific product. Follow label directions and seek clinician or pharmacist advice when unsure.

Is nighttime shoulder pain an emergency?

Usually not by itself. Emergency assessment is warranted when shoulder pain occurs with concerning chest or breathing symptoms, or when severe pain follows an injury with deformity, major swelling or inability to move the arm.

Categories Shoulder Pain, Frozen Shoulder

Frozen Shoulder vs Shoulder Injury: Understanding the Difference

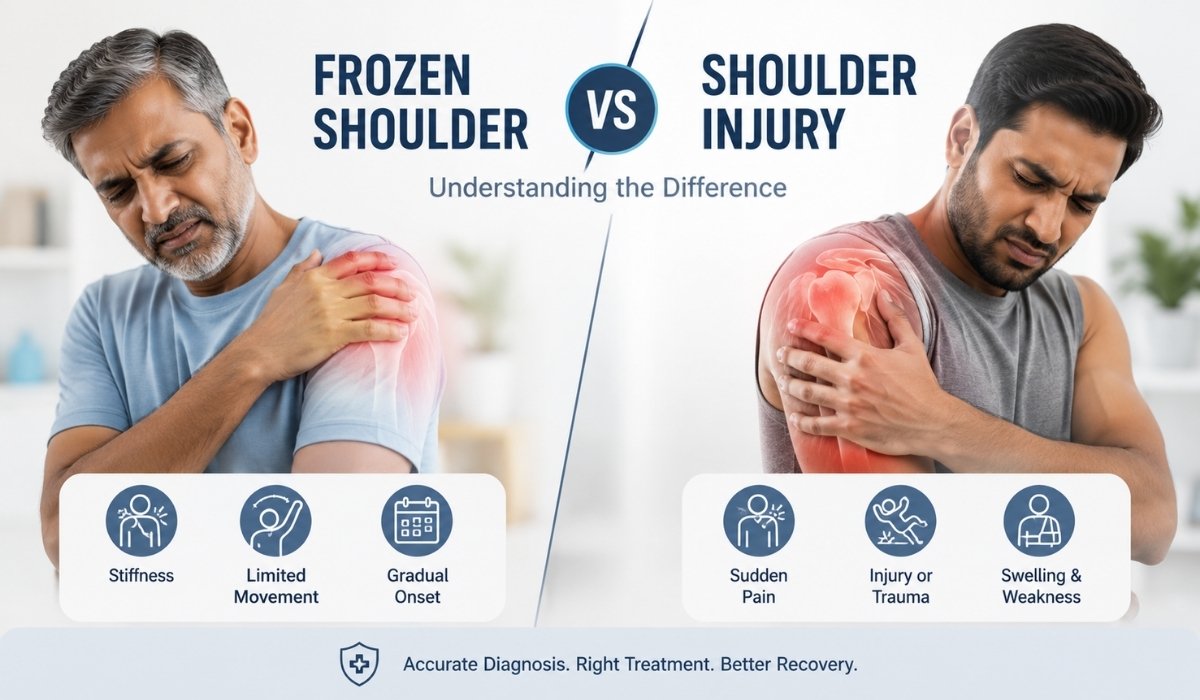
Illustration comparing frozen shoulder and shoulder injury, highlighting symptoms, pain areas, and limited shoulder movement.

Quick Answer

Frozen shoulder (adhesive capsulitis) is a stiffening and thickening of the shoulder joint capsule that restricts movement in every direction, including when someone else moves your arm for you. A shoulder injury — such as a rotator cuff tear, impingement, or strain — is damage to a specific muscle, tendon, or structure that usually causes pain and weakness with active movement, while passive movement (someone else lifting your arm) is often still possible. The passive range-of-motion test is the single biggest clue that separates the two.

Quick Summary

  • Frozen shoulder restricts movement in all directions, even with assistance; most shoulder injuries allow more passive movement than active movement.
  • Frozen shoulder usually develops gradually over weeks to months; injuries like rotator cuff tears can happen suddenly from a fall or lifting strain, or build up over years of overuse.
  • Frozen shoulder affects roughly 2–5% of the general population and is more common between ages 40–60, particularly in women and people with diabetes.
  • A rotator cuff tear can cause sharp pain and noticeable weakness, especially when raising the arm overhead; frozen shoulder pain is typically deep, diffuse, and worse at night.
  • Frozen shoulder progresses through three stages — freezing, frozen, and thawing — that can span months to a couple of years.
  • Imaging (ultrasound or MRI) helps confirm a structural injury and can also identify capsular thickening consistent with frozen shoulder.
  • Frozen shoulder is overwhelmingly managed without surgery, while some rotator cuff tears may eventually need surgical repair if conservative care fails.

Introduction

Shoulder pain is one of the most common reasons people in Ahmedabad visit a pain management clinic, and one of the most common points of confusion is whether the problem is a frozen shoulder or an underlying shoulder injury. Both can cause pain, stiffness, and difficulty sleeping on the affected side, but the underlying mechanism, expected recovery path, and treatment approach are quite different. Getting the distinction right early matters — treating a rotator cuff tear like a frozen shoulder, or vice versa, can delay real recovery by months.

This guide breaks down how frozen shoulder and shoulder injuries differ in symptoms, causes, diagnosis, and treatment, so you know what questions to ask before your consultation.

What Is Frozen Shoulder?

Frozen shoulder, medically known as adhesive capsulitis, occurs when the capsule of connective tissue surrounding the shoulder joint becomes inflamed, thickens, and tightens. This shrinks the space available for the joint to move, restricting motion in every direction — forward, backward, and sideways — regardless of whether the movement is active (done by the patient) or passive (assisted by someone else).

Expert Insight: In clinical practice, frozen shoulder is often missed in its early “freezing” stage because pain, not stiffness, is the dominant complaint at first. Patients frequently assume it’s a muscle strain and delay assessment until motion loss becomes obvious — by which point the stiffer “frozen” stage has already set in.

What Is a Shoulder Injury?

“Shoulder injury” is a broad term covering damage to a specific structure in the shoulder — most often the rotator cuff tendons, but also the labrum, bursa, or surrounding muscles. Common types include rotator cuff tears (partial or complete), shoulder impingement, tendinitis, and bursitis. Injuries can be acute (a fall, a heavy lift, a sports collision) or degenerative (built up gradually from repetitive overhead work, age-related wear, or occupations like painting, carpentry, or racquet sports).

Unlike frozen shoulder, most shoulder injuries leave passive range of motion relatively intact — a clinician or family member can often lift the arm through most of its normal arc, even though the patient cannot do it unassisted due to pain or weakness.

Symptoms: How to Tell Them Apart

The clearest bedside clue is the passive range-of-motion test: if someone else can lift your arm for you through a near-normal arc, an injury such as a rotator cuff tear is more likely. If the shoulder feels physically “locked” even with assistance, frozen shoulder is more likely.

FeatureFrozen ShoulderShoulder Injury (e.g. Rotator Cuff Tear)
OnsetGradual, over weeks to monthsOften sudden (fall, lift) or gradual overuse
Passive motionRestricted even with assistanceOften preserved with assistance
Pain characterDeep, diffuse ache, worse at nightSharp pain, often with specific movements
WeaknessUncommon as a primary symptomCommon, especially lifting overhead
ProgressionThree stages over months to ~2 yearsVaries; can worsen without treatment
Typical age group40–60 years, more common in womenAny age; higher in athletes and manual workers

Causes

Frozen shoulder causes include:

  • Idiopathic onset (no clear trigger) — the most common pattern
  • Prolonged immobilization after a prior injury, fracture, or surgery
  • Diabetes and thyroid disorders, which significantly raise risk
  • Underlying shoulder inflammation left untreated

Shoulder injury causes include:

  • Acute trauma — a fall onto an outstretched arm, sudden heavy lifting, or a sports collision
  • Repetitive overhead motion — swimming, painting, racquet sports, manual labour
  • Age-related degeneration of tendon tissue, which raises tear risk after the mid-40s
  • Poor posture and muscle imbalance contributing to impingement

Risk Factors

  • Age 40–60 (frozen shoulder); any age with repetitive strain (injuries)
  • Diabetes, thyroid disease, or cardiac conditions (frozen shoulder)
  • Recent shoulder or arm surgery, stroke, or a period of arm immobilisation
  • Occupations or sports requiring repetitive overhead arm movement
  • Previous shoulder injury that was not fully rehabilitated

Diagnosis

A thorough clinical examination is usually the starting point — comparing active versus passive range of motion, checking for specific weakness patterns, and reviewing how the pain began. Imaging plays a confirming role: an MRI or ultrasound can rule out or confirm a structural tear, and can occasionally show the capsular thickening characteristic of frozen shoulder. X-rays are sometimes used to rule out arthritis or bone spurs contributing to impingement.

Common Mistake: Self-diagnosing based on pain location alone. Pain in the same general area of the shoulder can come from the capsule, the tendons, the bursa, or even referred pain from the neck — a proper assessment is what actually separates these conditions.

Treatment Options

Treatment approaches diverge meaningfully once a diagnosis is confirmed.

Frozen ShoulderShoulder Injury
Physiotherapy focused on gentle, progressive stretchingPhysiotherapy focused on strengthening and controlled loading
Anti-inflammatory pain managementAnti-inflammatory pain management
Corticosteroid or hydrodilatation injections in select casesTargeted injections or PRP therapy for tendon healing
Radiofrequency ablation for select chronic pain casesRadiofrequency ablation for select chronic pain cases
Surgery rarely neededSurgery considered if conservative care fails or tear is complete

Non-Surgical Treatment Approaches

Most frozen shoulder cases, and a large share of shoulder injuries, respond well to non-surgical, interventional pain management. Structured physiotherapy, targeted injections, and image-guided procedures such as radiofrequency ablation or PRP therapy can meaningfully reduce pain and restore function without the recovery time associated with surgery. The right combination depends on the specific diagnosis, severity, and how long symptoms have been present.

Expert Insight: The earlier a frozen shoulder is correctly identified, the more responsive it tends to be to conservative treatment. Waiting through the freezing stage without intervention often means a longer, stiffer frozen stage before recovery begins.

Prevention Tips

  • Keep the shoulder moving through its normal range even after a minor injury — avoid unnecessary prolonged immobilisation
  • Manage diabetes and thyroid conditions proactively, as these directly raise frozen shoulder risk
  • Warm up before overhead activity and build shoulder and rotator cuff strength gradually
  • Seek assessment for shoulder pain that persists beyond 2–3 weeks rather than waiting it out
  • Complete any prescribed physiotherapy fully, even once pain improves, to avoid re-injury or stiffness

Recovery and Rehabilitation

Frozen shoulder recovery is typically the slower of the two, often spanning several months to around two years across its freezing, frozen, and thawing stages, though most patients see steady improvement with consistent physiotherapy. Shoulder injury recovery timelines vary more widely — mild strains and tendinitis often improve within 4–8 weeks of guided rehabilitation, while a significant rotator cuff tear, if treated conservatively, may take 3–6 months to regain full strength, and longer if surgery is required.

Common Mistake: Stopping rehabilitation exercises as soon as pain eases. Pain relief is not the same as full recovery — stopping early is one of the most frequent reasons stiffness or weakness returns.

Expert Insight: When Both Conditions Overlap

It is possible to have a rotator cuff injury and later develop frozen shoulder, particularly if the arm was kept still for an extended period during recovery. This is why ongoing follow-up matters even after an initial injury has been treated.

Common Mistakes Patients Make

  • Assuming all shoulder pain is “just a strain” and delaying evaluation for months
  • Relying only on painkillers without addressing the underlying stiffness or structural cause
  • Over-resting the shoulder for frozen shoulder, which can worsen stiffness rather than help it

Myths vs Facts

MythFact
Frozen shoulder always needs surgery.Most cases improve with physiotherapy and non-surgical pain management; surgery is uncommon.
If you can move your arm at all, it can’t be frozen shoulder.Some limited active movement is still possible, especially in early stages; the key marker is restricted passive movement.
Rest is always best for shoulder pain.Complete immobilisation can worsen or trigger frozen shoulder; guided, gentle movement is usually recommended instead.
A rotator cuff tear always requires surgery.Many tears, especially partial ones, respond well to physiotherapy and interventional treatment first.

Questions Patients Forget to Ask

  • Is my shoulder pain coming from the joint capsule, a tendon, or somewhere else, like my neck?
  • What stage is my frozen shoulder in, and how does that change my treatment plan?
  • Will imaging actually change my treatment, or is a clinical exam enough for now?
  • What specific home exercises are safe for my exact diagnosis, and which should I avoid?
  • At what point would we consider an injection, PRP, or radiofrequency ablation instead of continuing physiotherapy alone?

Practical Action Plan

  1. If shoulder pain or stiffness has lasted more than 2–3 weeks, book a clinical assessment rather than waiting it out.
  2. Note whether someone else can lift your arm for you comfortably — this detail helps guide the initial diagnosis.
  3. Avoid prolonged immobilisation; keep the shoulder gently mobile unless specifically advised otherwise.
  4. Ask your clinician whether imaging is needed to confirm a structural injury or capsular thickening.
  5. Follow the full physiotherapy course prescribed, even after pain starts improving.
  6. Discuss non-surgical options — physiotherapy, injections, PRP, or radiofrequency ablation — before considering surgery.

Nexus Pain Expert Summary Box

Distinguishing frozen shoulder from a shoulder injury starts with a comprehensive pain assessment that looks at active versus passive movement, pain pattern, and relevant risk factors such as diabetes or a prior injury. Based on that assessment, an evidence-based, personalised treatment plan can combine physiotherapy guidance, non-surgical interventional pain procedures, and long-term rehabilitation support — with the goal of restoring shoulder function without unnecessary surgery wherever possible. Lifestyle and movement guidance is also provided to reduce the chance of recurrence.

Key Takeaways

  • Frozen shoulder restricts both active and passive movement; most injuries mainly limit active movement.
  • Onset is gradual for frozen shoulder, often sudden for acute injuries like tears.
  • Diabetes, thyroid conditions, and prior immobilisation raise frozen shoulder risk.
  • A proper clinical exam, and imaging when needed, is the reliable way to tell the two apart.
  • Both conditions usually respond to non-surgical, physiotherapy-led treatment when caught early.
  • Delaying assessment tends to prolong recovery for either condition.
  • Recovery timelines differ significantly, so an accurate diagnosis sets realistic expectations.

Frequently Asked Questions

  1. What is the main difference between frozen shoulder and a shoulder injury?

Frozen shoulder restricts movement in every direction, even when someone else moves your arm for you, because the joint capsule itself has tightened. A shoulder injury, such as a rotator cuff tear, usually still allows passive movement even when active movement is painful or weak.

  1. Can a shoulder injury turn into frozen shoulder?

Yes. Prolonged immobilisation after an injury or surgery is a recognised risk factor for developing frozen shoulder afterward, which is why gentle, guided movement during recovery matters.

  1. How long does frozen shoulder usually last?

Frozen shoulder typically progresses through freezing, frozen, and thawing stages over several months to around two years, though consistent physiotherapy can support steadier improvement.

  1. Is frozen shoulder more common in people with diabetes?

Yes, diabetes is a well-established risk factor for frozen shoulder, along with thyroid disorders and periods of shoulder immobilisation.

  1. Does a rotator cuff tear always need surgery?

Not always. Many tears, particularly partial ones, are managed successfully with physiotherapy and non-surgical pain management before surgery is considered.

  1. What does the “passive range of motion” test actually check?

It checks whether someone else can move your arm through its normal range for you. Preserved passive motion points more toward an injury like a tear; restricted passive motion points more toward frozen shoulder.

  1. Can I have both a rotator cuff injury and frozen shoulder at the same time?

Yes, this combination does occur, which is one reason accurate clinical assessment is important rather than assuming just one condition is present.

  1. Is shoulder pain that’s worse at night more typical of frozen shoulder or an injury?

Night pain is common in both, but the deep, diffuse ache of frozen shoulder disrupting sleep is a classic pattern, while injury-related night pain often relates to specific sleeping positions that load the tendon.

  1. What tests are used to diagnose frozen shoulder versus a shoulder injury?

A clinical exam comparing active and passive movement is the starting point; ultrasound or MRI can then confirm a structural tear or show capsular thickening if the diagnosis remains unclear.

  1. Is exercise safe for frozen shoulder, or should the shoulder be rested?

Gentle, guided movement is generally recommended over complete rest, since prolonged immobilisation can worsen stiffness. Exercises should be tailored to your specific stage and diagnosis.

  1. When should I see a pain management specialist for shoulder pain?

If shoulder pain or stiffness has persisted beyond 2–3 weeks, is limiting daily activities, or is affecting sleep, it’s worth getting a clinical assessment rather than waiting for it to resolve on its own.

  1. Where can I get frozen shoulder or shoulder injury treatment in Ahmedabad?

Nexus Pain Management in Ahmedabad offers comprehensive shoulder pain assessment and evidence-based, non-surgical treatment planning, including physiotherapy guidance and interventional pain procedures where appropriate.

Categories Shoulder Pain

Comprehensive Insights on Shoulder Pain Treatment: Regain Mobility and Comfort

Shoulder pain can range from a minor inconvenience to a debilitating condition, significantly affecting your daily activities. This complex joint is essential for upper body mobility, and pain in this area can arise from various causes. In this blog, we delve into the common causes of shoulder pain, available treatment options, and strategies for long-term relief.

Causes of Shoulder Pain

Shoulder pain often originates from the following factors:

  • Rotator Cuff Injuries: Tears or inflammation in the rotator cuff can limit movement and cause significant discomfort.
  • Frozen Shoulder (Adhesive Capsulitis): Characterized by stiffness and restricted motion.
  • Shoulder Impingement: Occurs when tendons are pinched during shoulder movements.
  • Arthritis: Degenerative changes in the joint can lead to chronic pain and reduced mobility.
  • Fractures or Dislocations: Injuries can disrupt the normal structure and function of the shoulder.
  • Bursitis or Tendinitis: Inflammation of the bursa or tendons due to overuse or repetitive motion.

Identifying the underlying cause is essential for effective treatment and lasting relief. Consulting a specialist ensures a precise diagnosis and tailored treatment approach.

Effective Treatments for Shoulder Pain

  1. Physical Therapy:
    • Stretching and strengthening exercises help improve mobility and reduce stiffness.
    • Techniques focus on restoring range of motion and preventing future injuries.
  2. Medications:
    • Nonsteroidal anti-inflammatory drugs (NSAIDs) like ibuprofen can alleviate inflammation and pain.
    • Muscle relaxants or prescription medications may be necessary for severe cases.
  3. Interventional Treatments:
    • Corticosteroid Injections: Reduce inflammation and provide quick relief.
    • PRP Therapy (Platelet-Rich Plasma): Promotes healing by using the body’s own growth factors.
  4. Advanced Procedures:
    • Arthroscopy: Minimally invasive surgery to repair structural damage.
    • Joint Replacement Surgery: Considered for severe arthritis or irreparable joint damage.
  5. Lifestyle Adjustments:
    • Avoid repetitive overhead movements that strain the shoulder.
    • Maintain proper posture to reduce unnecessary pressure on the joint.
  6. Alternative Therapies:
    • Acupuncture: Stimulates specific points to reduce pain and improve function.
    • Chiropractic Adjustments: Correct misalignments and relieve stress on the shoulder.

Preventing Shoulder Pain

  • Warm up before engaging in physical activity.
  • Strengthen shoulder muscles through targeted exercises.
  • Avoid carrying heavy bags on one shoulder for extended periods.
  • Take breaks during repetitive tasks to prevent overuse injuries.

Conclusion

Shoulder pain doesn’t have to limit your life. At Nexus Advanced Pain Management, we provide expert diagnosis and personalized treatments to address the root causes of shoulder pain. With our comprehensive care, you can regain your mobility and enjoy a pain-free life. Trust Nexus Advanced Pain Management to guide you on your journey to recovery and long-term comfort.