
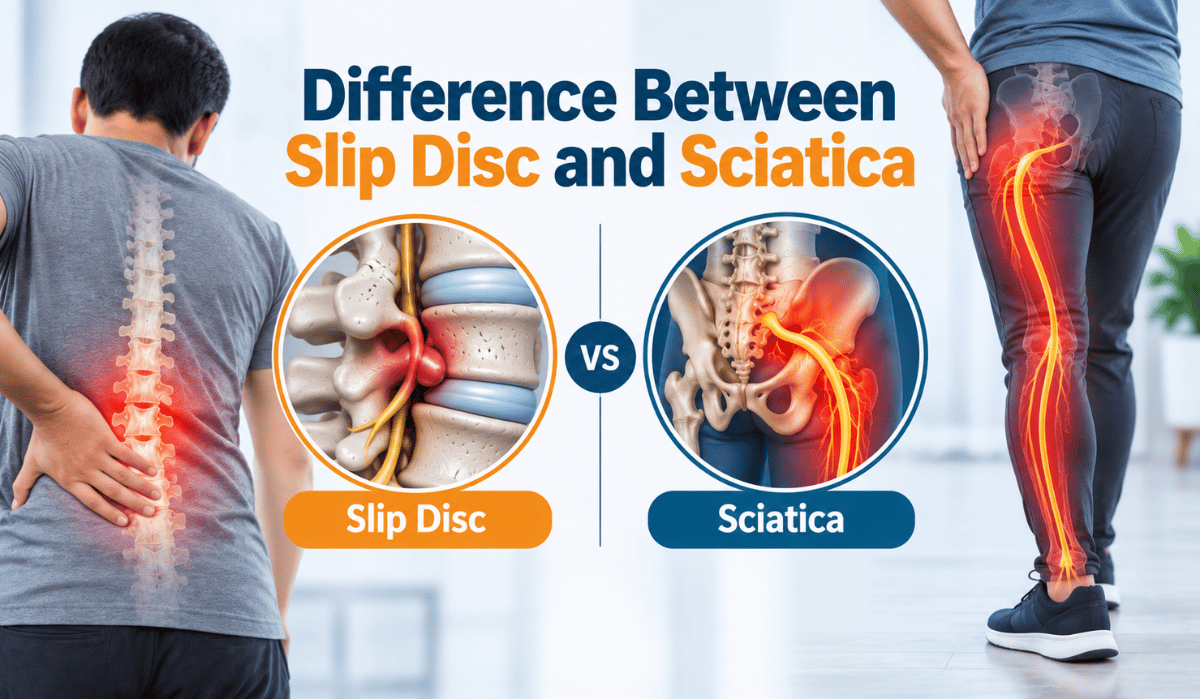

Quick Answer
A slip disc (herniated or prolapsed disc) is a structural problem in the spine, where the cushion between two vertebrae bulges or ruptures. Sciatica is not a disease by itself — it is a pattern of nerve pain that travels along the sciatic nerve, from the lower back through the buttock and down the leg. A slip disc is one of the most common causes of sciatica, but sciatica can also occur without any disc problem, and a slip disc does not always cause sciatica. The distinction matters because it changes how the condition is diagnosed and treated.
Quick Summary
- A slip disc is a condition affecting the spinal disc; sciatica is a symptom of nerve irritation, not a disease on its own.
- A slip disc can occur without ever causing sciatica — many disc bulges are found on scans without any nerve symptoms.
- Sciatica can also happen without a slip disc, caused instead by piriformis syndrome, spinal stenosis, or spondylolisthesis.
- Slip disc pain is often localized to the back; sciatica pain travels along a specific nerve path into the buttock, leg, or foot.
- Doctors use tests such as the straight-leg-raise test and dermatome mapping, alongside history and examination, before considering an MRI.
- Most sciatica improves within four to six weeks with conservative, non-surgical care.
- Warning signs such as saddle numbness or new bladder or bowel changes need urgent medical attention, regardless of the underlying cause.
Introduction
If you have lower back pain that shoots down your leg, you have probably already searched online and found two terms used almost interchangeably: slip disc and sciatica. This confusion is understandable — the two conditions overlap often enough that even the pain pattern can feel identical. But they are not the same thing, and understanding the difference genuinely changes how a doctor evaluates and treats you. This guide breaks down what each condition actually is, how they relate to each other, how they are diagnosed, and what evidence-based, non-surgical treatment options typically look like.
What Is a Slip Disc?
A slip disc, medically called a herniated, prolapsed, or ruptured disc, occurs when the soft inner core (nucleus pulposus) of a spinal disc pushes out through a tear in its tougher outer layer (annulus fibrosus). It most commonly affects the lower back (lumbar spine), particularly the L4-L5 and L5-S1 discs, though it can occur in the neck as well.
Disc problems exist on a spectrum, from a mild bulge to a fully displaced fragment. Radiologists generally describe them as a bulge, protrusion, extrusion, or sequestration, depending on how far the disc material has moved and whether it has separated from the parent disc. This matters clinically because the degree of herniation often (though not always) correlates with symptom severity, and it is one of the details an MRI report will specify.
| Expert Insight “Not every slip disc seen on an MRI is the cause of a patient’s pain. Disc bulges are extremely common with age and are frequently found incidentally on scans done for unrelated reasons. This is why we always correlate imaging findings with the patient’s actual symptoms and physical examination, rather than treating the scan in isolation.” |
What Is Sciatica?
Sciatica refers to pain that follows the path of the sciatic nerve — the longest and widest nerve in the body, running from the lower spine through the buttock and down the back of the leg. Sciatica is a symptom, not a diagnosis in itself. It develops when a nerve root feeding into the sciatic nerve is compressed or irritated.
A slip disc is the most common cause of sciatica, but it is far from the only one. Other causes include:
- Spinal stenosis — narrowing of the spinal canal, more common in older adults
- Spondylolisthesis — one vertebra slipping forward over the one below it
- Piriformis syndrome — a deep buttock muscle spasming and irritating the nerve
- Bone spurs or age-related degenerative changes in the spine
This is the central point most patients miss: you can have sciatica without ever having a slip disc, and you can have a slip disc without ever developing sciatica.
Key Difference: Condition vs Symptom
The clearest way to separate the two is this: a slip disc is a structural, physical injury to the spine. Sciatica is a pattern of nerve pain that can result from that injury, or from something else entirely.
| Aspect | Slip Disc | Sciatica |
| Nature | A structural spinal condition | A symptom pattern, not a disease itself |
| Where pain is felt | Often localized to the back; may or may not radiate | Travels along the sciatic nerve into buttock, leg, or foot |
| Common causes | Age-related wear, heavy lifting, injury, repeated strain | Slip disc, spinal stenosis, spondylolisthesis, piriformis syndrome |
| Typical pattern | Can be central or one-sided; worsens with bending or lifting | Usually one-sided; worsens with sitting, coughing, or sneezing |
| Diagnosis | MRI or CT imaging when clinically indicated | Clinical exam, straight-leg-raise test, dermatome mapping |
Symptoms
Slip Disc Symptoms
- Localized back or neck pain, sometimes described as a deep ache
- Pain that worsens with bending, lifting, coughing, or sitting for long periods
- Stiffness or reduced range of motion in the spine
- In some cases, no symptoms at all — many disc bulges are found incidentally
Sciatica Symptoms
- Sharp, shooting, or burning pain radiating from the lower back through the buttock and leg
- Numbness, tingling, or a ‘pins and needles’ sensation along the nerve path
- Muscle weakness in the affected leg, or a leg that feels heavy
- Symptoms typically affecting one side of the body
Causes
Slip disc causes typically include age-related disc degeneration, repetitive strain, improper lifting technique, sudden twisting injuries, and excess body weight placing added load on the spine. Smoking is also associated with faster disc degeneration.
Sciatica causes trace back to whatever is compressing or irritating the sciatic nerve root — most often a slip disc, but also spinal stenosis, spondylolisthesis, piriformis syndrome, or, less commonly, a spinal tumour or infection.
Risk Factors
- Age between 30 and 50 years for disc herniation; sciatica risk rises further with age due to degenerative changes
- Jobs involving heavy lifting, prolonged sitting, or repetitive twisting motions
- Sedentary lifestyle with weak core and back-supporting muscles
- Obesity, which increases mechanical load on the lower spine
- Smoking, which accelerates disc degeneration
- Previous back injury or a family history of spinal disc problems
Diagnosis
Diagnosis begins with a detailed history and physical examination — most cases of sciatica can be identified clinically before any imaging is needed. A doctor will typically assess:
- Pain pattern and distribution, checked against known dermatome maps for the L4, L5, and S1 nerve roots
- The straight-leg-raise (Lasègue’s) test — pain reproduced between roughly 30° and 70° of hip flexion suggests nerve root irritation
- Reflexes at the knee and ankle, and muscle strength testing (for example, weakness in big-toe extension can point to an L5 issue)
- Red-flag screening for rare but urgent causes requiring immediate care
MRI is the imaging test of choice when it is needed, but current clinical guidance is clear that imaging is not routinely required for every case of back or leg pain. It is generally reserved for red-flag symptoms, pain that fails to improve after a reasonable trial of conservative treatment, or when a procedure is being planned.
| When to Seek Urgent Care Certain symptoms need same-day medical attention regardless of whether the cause is a slip disc or something else: numbness in the saddle area (inner thighs, groin), new difficulty controlling the bladder or bowels, or rapidly worsening leg weakness. These can indicate cauda equina syndrome, a rare but time-sensitive emergency. |
Treatment Options
Treatment is guided by the underlying cause, symptom severity, and how the individual is responding over time — not by the label alone. For both slip disc and sciatica, the majority of patients improve without surgery.
Non-Surgical Treatment
- Activity modification and short-term rest from aggravating movements, while staying generally active
- Physiotherapy focused on core strengthening, flexibility, and posture correction
- Oral anti-inflammatory or nerve-pain medication, prescribed and monitored by a physician
- Interventional pain procedures such as epidural steroid injections for persistent nerve-related pain
- Radiofrequency ablation for select cases of chronic pain not responding to first-line care
- Lifestyle changes: ergonomic adjustments, weight management, and structured exercise
Surgery is considered a later option, generally after a reasonable trial of conservative, non-surgical treatment — typically extending to three months or more — has not provided adequate relief of disabling leg pain, or if there are red-flag findings such as progressive neurological weakness.
| Expert Insight “Patients often ask whether a slip disc always needs surgery. In most cases, it does not. A structured non-surgical program — physiotherapy, activity modification, and, where appropriate, targeted interventional procedures — resolves the majority of cases. Surgery is reserved for a smaller subset where conservative care has genuinely been given a fair trial and has not worked, or where there are clear neurological red flags.” |
Prevention Tips
- Use proper lifting technique: bend at the knees and hips, not the waist, and keep the load close to your body
- Maintain a strengthening routine for core and back-supporting muscles
- Avoid prolonged sitting; take short movement breaks every 30 to 45 minutes
- Maintain a healthy body weight to reduce load on the lumbar spine
- Correct your workstation ergonomics — screen height, chair support, and desk posture
- Avoid smoking, which is linked to faster disc degeneration
Recovery and Rehabilitation
Recovery timelines vary by individual and severity, but as a general pattern, most people with sciatica notice meaningful improvement within four to six weeks of starting conservative treatment. Slip disc recovery can take longer, particularly if physiotherapy and activity modification are needed to rebuild strength and prevent recurrence. Gradual return to normal activity, guided rehabilitation exercises, and consistent posture habits are typically more effective for long-term outcomes than prolonged rest.
| Common Mistake Many patients either rest too much, fearing that any movement will worsen a slip disc, or return to heavy activity too soon once the sharp pain fades. Both approaches can slow recovery. Prolonged bed rest weakens supporting muscles, while premature heavy lifting can trigger a flare-up before the disc and nerve have adequately healed. |
Expert Insight: On Imaging and Overtreatment
A frequent concern we see is patients requesting an MRI at the very first visit, assuming imaging will immediately clarify everything. In reality, MRI findings such as disc bulges are extremely common in people with no pain at all, so an image alone can be misleading without a matching clinical picture. A careful history and examination remain the foundation of an accurate diagnosis, with imaging used selectively rather than as a first step for everyone.
Common Mistakes Patients Make
- Assuming any back pain that travels to the leg is automatically a slip disc, when several other conditions can cause identical sciatica symptoms.
- Skipping physiotherapy because the pain has temporarily eased, which increases the risk of recurrence.
- Self-medicating with painkillers for weeks without a proper diagnosis, delaying appropriate treatment.
- Requesting or expecting an MRI before a clinical evaluation, even when imaging is not yet indicated.
- Believing surgery is the only real solution, when most cases respond well to non-surgical, evidence-based care.
Myths vs Facts
| Myth | Fact |
| A slip disc always causes sciatica. | Many disc bulges or herniations are asymptomatic and cause no nerve pain at all. |
| Sciatica means you definitely have a slip disc. | Sciatica can result from piriformis syndrome, spinal stenosis, or spondylolisthesis, with no disc involvement. |
| Surgery is the only permanent fix. | Most patients improve significantly with structured non-surgical treatment. |
| Complete bed rest speeds up healing. | Staying appropriately active generally supports better, faster recovery than prolonged rest. |
| An MRI is needed to confirm every case. | Imaging is often unnecessary early on and is reserved for red flags or non-improving cases. |
Questions Patients Forget to Ask
- Is my pain coming from the disc itself, or from nerve irritation caused by something else?
- What specific exercises should I avoid right now, and which ones are safe to continue?
- How will we know if conservative treatment is working, and by when should I expect improvement?
- What red-flag symptoms should prompt me to seek immediate care rather than waiting for my next appointment?
- If imaging is recommended, how will the result actually change my treatment plan?
Practical Action Plan
- Track your symptoms: note where the pain is felt, whether it radiates, and what movements worsen or ease it.
- See a pain specialist or spine doctor for a clinical evaluation rather than self-diagnosing from symptoms alone.
- Stay appropriately active — avoid both complete bed rest and activities that clearly aggravate symptoms.
- Begin guided physiotherapy early rather than waiting for the pain to become severe.
- Reassess with your doctor if there is no meaningful improvement within four to six weeks, or sooner if red-flag symptoms appear.
Nexus Advanced Pain Management Expert Summary
A slip disc and sciatica are related but distinct: one is a structural spinal problem, the other is a nerve pain pattern that may or may not stem from it. Accurate diagnosis — built on a careful history, physical examination, and imaging only when genuinely indicated — is what determines the right, evidence-based treatment path. Most patients can expect meaningful improvement with structured non-surgical care.
How Nexus Advanced Pain Management Can Help
Nexus Advanced Pain Management approaches back and leg pain through a comprehensive pain assessment that looks beyond imaging alone to understand the actual source of symptoms. This includes evidence-based treatment planning tailored to whether the presentation points to a structural disc problem, nerve irritation, or both.
Care typically involves non-surgical pain management as a first line of treatment, with interventional pain procedures such as epidural injections or radiofrequency ablation considered for select patients whose symptoms persist despite conservative care. Every treatment plan is built around personalized goals, with attention to rehabilitation guidance and lifestyle modification support so that recovery is sustainable rather than temporary. The focus throughout remains on long-term pain relief strategies rather than short-term symptom masking.
Key Takeaways
- A slip disc is a structural condition; sciatica is a nerve pain symptom, and the two do not always occur together.
- Sciatica can arise from causes other than a slip disc, including piriformis syndrome and spinal stenosis.
- Clinical examination, including the straight-leg-raise test, is usually the first step in diagnosis — not imaging.
- Most cases of both slip disc and sciatica improve with structured non-surgical treatment.
- Staying appropriately active supports recovery better than prolonged bed rest.
- Red-flag symptoms like saddle numbness or bladder changes require immediate medical attention.
- Surgery is reserved for cases that do not respond to an adequate trial of conservative care, or where red flags are present.
Frequently Asked Questions
Is a slip disc the same as sciatica?
No. A slip disc is a structural spinal condition, while sciatica is a pattern of nerve pain that a slip disc can cause, but does not always cause.
Can you have sciatica without a slip disc?
Yes. Sciatica can result from spinal stenosis, spondylolisthesis, piriformis syndrome, or age-related degenerative changes, without any disc herniation present.
Can a slip disc heal without surgery?
Many slip discs improve with non-surgical treatment such as physiotherapy, activity modification, and, when needed, interventional pain procedures. Surgery is considered only if conservative treatment does not provide adequate relief.
How long does sciatica usually last?
Many people notice meaningful improvement within four to six weeks of starting appropriate conservative treatment, though timelines vary by individual and cause.
What test confirms sciatica?
There is no single definitive test. Doctors combine history, physical examination findings such as the straight-leg-raise test, and dermatome assessment; imaging is used selectively rather than routinely.
Is walking good for sciatica or a slip disc?
Gentle, appropriately paced walking is generally encouraged as part of staying active, though a doctor or physiotherapist should tailor activity recommendations to your specific presentation.
When should I worry about sciatica symptoms?
Seek urgent care if you notice numbness in the saddle area, new difficulty controlling your bladder or bowels, or rapidly worsening leg weakness.
Does a slip disc always show up on an MRI?
MRI can detect most disc herniations, but many people without any pain also have disc bulges visible on MRI, so findings must be correlated with symptoms.
What is the difference between sciatica and piriformis syndrome?
Both cause similar buttock and leg pain, but sciatica from piriformis syndrome originates from muscle irritation of the nerve rather than a spinal disc problem, and often requires a different treatment focus.
Can sitting for long hours cause a slip disc or sciatica?
Prolonged sitting increases pressure on the lower spinal discs and is a recognized risk factor for both disc problems and the onset of sciatic nerve irritation.
Where can I get evaluated for slip disc or sciatica symptoms in Ahmedabad?
Nexus Advanced Pain Management provides comprehensive evaluation for back and leg pain, including assessment for slip disc and sciatica, at its Ahmedabad clinic.
Is surgery always required for a herniated disc with sciatica?
No. The majority of patients improve with non-surgical treatment. Surgery is typically reserved for cases with disabling pain that has not responded to an adequate trial of conservative care, or for specific neurological red flags.